

Thirteen years ago, Maryland adopted a different approach to care under Medicaid.
On September 18, 2013, CMS approved the Maryland Health Home plan. The amendment to the State Plan came into effect on October 1, 2013. The Maryland Health Home model was established under Section 2703 of the Affordable Care Act (ACA).
The real question was what was to be achieved through this program?
It was quite simple. The goal was to bring all relevant care under one integrated system, rather than separating a patient’s different needs into separate boxes.
Health Homes were created so that patients could receive care with better coordination across physical health, mental and behavioral health, substance use disorder treatment, and community-based services.
People eligible for this type of benefit, for example, may include:
- People diagnosed with Serious Mental Illness (SMI);
- Those with Serious Emotional Disturbance (SED);
- People with Substance Use Disorders (SUD).
States were also given additional federal financial support to establish such programs. For the first eight quarters following the program’s implementation, states were to receive an enhanced Federal Medical Assistance Percentage (FMAP) rate of 90 percent.
The additional money was intended to provide a substantial financial incentive for Maryland to adopt and implement this approach.
Thirteen years later, the program is still running.
And although it may seem obvious, there is one document that HHAs, MDs, PTs, OTs, SLPs, MSWs, and PCAs cannot afford to overlook: The “Maryland Medicaid Fee Schedule”
Note: “Health Home” and “Home Health” are not the same thing.
Many people get confused by the term “Health Home,” because it may sound like the name of a residence or facility where nursing or personal care services are provided. However, a Medicaid Health Home is not that.
A Health Home has a care coordinator who establishes a link between the various services the patient receives. Essentially, this person connects all of the patient’s medical service providers.
This may include coordinating medication management, providing access to mental and behavioral health services, substance use disorder treatment, and other supportive services available in the community.
The goal of the Maryland Health Home Program is to assist Medicaid beneficiaries who have chronic illnesses or unmet needs resulting from serious mental and behavioral health conditions. One of the primary objectives of this program is to integrate treatment so that the entire medical care system works as one coordinated entity instead of several practitioners working separately on different issues.
The Maryland Health Home Medicaid rates for Fiscal Year 2026 list the CPT codes, modifiers, corresponding payment rates, and claim submission instructions for each reimbursable service.
Before looking at the data, keep in mind one key difference:
- Health Home = Coordination among the patient’s different medical and support services.
- Home Health = Provision of medical, nursing, or supportive care services in the patient’s own home.
Do not confuse the two.
| Differences | Health Home | Home Health |
| What it is | A care-coordination program, delivered through a PRP, MTS, or OTP provider | A skilled clinical service, like nursing or physical therapy, delivered in someone’s residence |
| Where care happens | An office, clinic, mobile unit, or similar approved site | The patient’s own home |
| What it pays for | Coordinating and managing a person’s overall behavioral and physical healthcare | Hands-on skilled services, wound care, injections, physical/occupational therapy, skilled nursing visits |
| Billing codes covered in this article | W1760, W1761, W1762 | Not covered here.An entirely separate program and fee schedule |
| Who bills it | PRP, MTS, OTP programs | Licensed home health agencies |
Maryland Medicaid FY2026 Health Home Reimbursement Structure
Three codes are used for Health Home payments in Maryland, and each has a different purpose:
- W1762 — To record the specific work performed and the progress made.
- W1761 — For ongoing continuing care each month.
- W1760 — To enroll the patient in the program.
The first two codes, W1761 and W1762, carry the same payment rate, but both are used in different situations and have separate rules. That is why some service providers find these codes confusing.
Think of it in a simple way:
- W1760 is like opening the door for the first time — the patient is being included in the program.
- W1761 is like keeping the system running month after month — maintaining continuous care and contact with the patient.
- And W1762 is the written evidence that tells what actually happened, what service or action was performed, and how the activity was documented.
| Procedure Code | Purpose | FY2026 Rate | Billing Frequency | Modifier | Key Billing Requirement | Timely Filing | OTP POS | PRP POS | MTS POS |
| W1760 | Intake Assessment or Enrollment | $145.76 | One-time | None specified | Used for initial Health Home enrollment. Does not count toward the two-service requirement for W1761. Rebilling is subject to applicable re-enrollment and transfer rules. | – | 58, 11, 15, 49 | 11, 49, 52, 15 | 11, 15, 49 |
| W1761 | Monthly Health Home Services | $145.76 | Once per month | None specified | Participant must receive at least 2 qualifying core Health Home services during the service month. | Within 30 days after the end of the service month | 58, 11, 15, 49 | 11, 49, 52, 15 | 11, 15, 49 |
| W1762 | Service Documentation / Core Service Designation | Non-billable | As applicable to monthly services | H1–H6 | Identifies the specific core Health Home service provided and supports the two-service requirement for W1761. | Within 30 days after the end of the service month | 58, 11, 15, 49 | 11, 49, 52, 15 | 11, 15, 49 |
Terms You Should Understand Regarding Maryland Health Home Billing
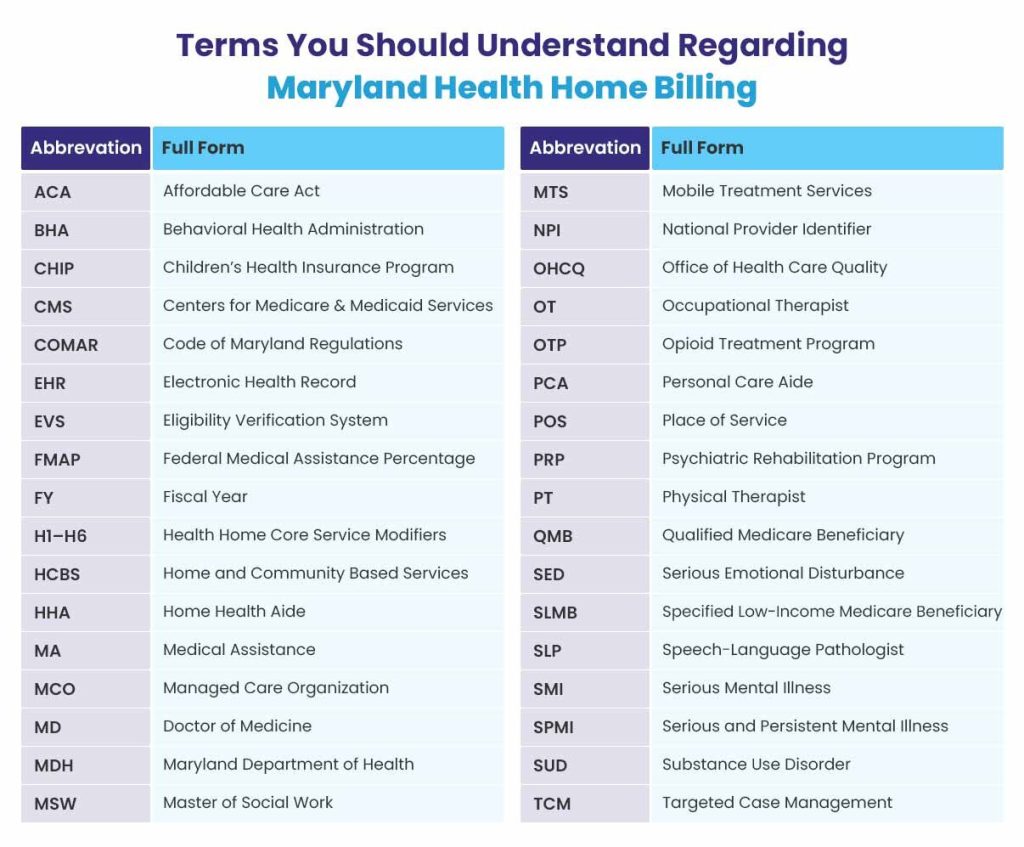
Uncertain about the meaning of PRP, MTS, OTP, or POS? The main acronyms used in Maryland’s FY2026 Health Home billing standards are explained in this brief dictionary.
| Abbrevation | Full Form |
| ACA | Affordable Care Act |
| BHA | Behavioral Health Administration |
| CHIP | Children’s Health Insurance Program |
| CMS | Centers for Medicare & Medicaid Services |
| COMAR | Code of Maryland Regulations |
| EHR | Electronic Health Record |
| EVS | Eligibility Verification System |
| FMAP | Federal Medical Assistance Percentage |
| FY | Fiscal Year |
| H1–H6 | Health Home Core Service Modifiers |
| HCBS | Home and Community-Based Services |
| HHA | Home Health Aide |
| MA | Medical Assistance |
| MCO | Managed Care Organization |
| MD | Doctor of Medicine |
| MDH | Maryland Department of Health |
| MSW | Master of Social Work |
| MTS | Mobile Treatment Services |
| NPI | National Provider Identifier |
| OHCQ | Office of Health Care Quality |
| OT | Occupational Therapist |
| OTP | Opioid Treatment Program |
| PCA | Personal Care Aide |
| POS | Place of Service |
| PRP | Psychiatric Rehabilitation Program |
| PT | Physical Therapist |
| QMB | Qualified Medicare Beneficiary |
| SED | Serious Emotional Disturbance |
| SLMB | Specified Low-Income Medicare Beneficiary |
| SLP | Speech-Language Pathologist |
| SMI | Serious Mental Illness |
| SPMI | Serious and Persistent Mental Illness |
| SUD | Substance Use Disorder |
| TCM | Targeted Case Management |
W1760: Initial Assessment and Enrollment — $145.76
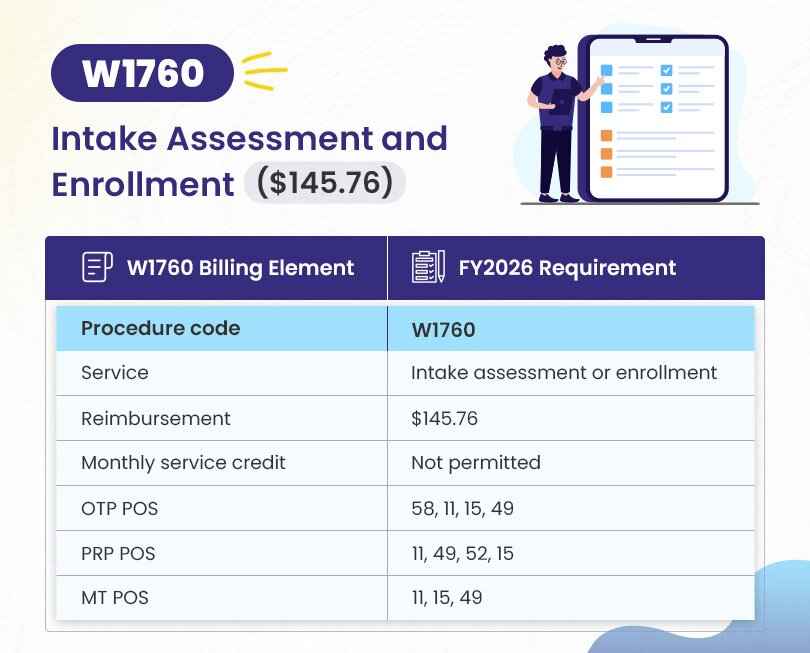
W1760 is a one-time use code. This means that whenever an individual completes the assessment and is enrolled in the Health Home program, a payment of $145.76 is recorded.
The most important thing about this code is that no separate monthly service payment can be claimed for the same month. In other words, the separate W1760 payment is generated based on the enrollment date, and no additional monthly payment is recorded for other Health Home services provided during that same month.
Subsequent payments will cease when the service provider discontinues participation in the Health Home program.
The exact Place of Service codes acceptable for payment are:
- OTP, or Opioid Treatment Programs: 58, 11, 15, and 49
- PRP, or Psychiatric Rehabilitation Program: 11, 49, 52, and 15
- MT, or Mobile Treatment: 11, 15, and 49
| W1760 Billing Element | FY2026 Requirement |
| Procedure code | W1760 |
| Service | Intake assessment or enrollment |
| Reimbursement | $145.76 |
| Monthly service credit | Not permitted |
| OTP POS | 58, 11, 15, 49 |
| PRP POS | 11, 49, 52, 15 |
| MT POS | 11, 15, 49 |
See, one important distinction here is that PRP has an additional Place of Service code, 52, which does not apply to OTP or MT. Therefore, it is advisable to set up an alert in your billing system for PRP claims so that you are immediately notified if a claim is rejected because of an incorrect location or setting.
✅ Important Note for Providers Regarding W1760: Compliance With Initial Enrollment Claim Rules
W1760 cannot be used more than once for the same member without meeting Maryland Medicaid’s re-enrollment or transfer requirements.
➜ New Member: A new member is enrolled in the Health Home program, and W1760 is recorded.
➜ Member Re-Enrolling With the Same Provider: If a member is discharged from the program and later returns to the same Health Home, W1760 cannot be billed again until at least 90 days have passed since the discharge.
➜ When a Member Relocates to Another Health Home: A new provider may bill W1760 if the member was discharged at least 90 days earlier or if six months have passed since the member’s original initial enrollment.
➜ Internal Review: MDH advises that claims submitted under W1760 since January 1, 2025, be internally reviewed to identify potential overpayments.
➜ Overpayment: If an overpayment is identified, the provider must refund the amount and correct the matter in accordance with Maryland Medicaid regulations.
W1761: Monthly Health Home Services — $145.76
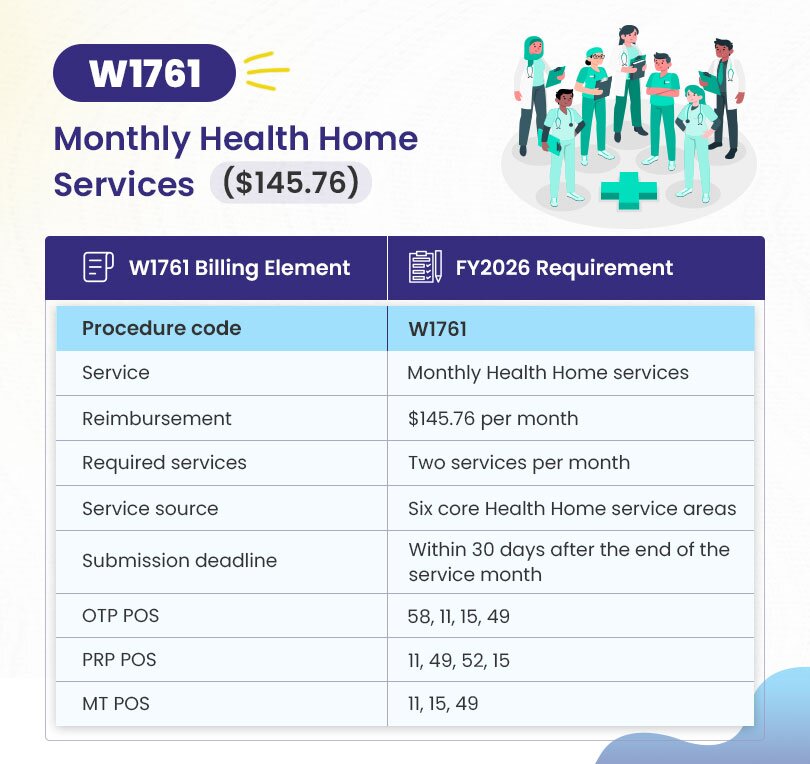
This is your monthly payment code. It is used once a month, and the payment amount is $145.76.
But there are some important restrictions regarding the use of this code. To bill using W1761, the individual receiving services from your organization must have received at least two billable Health Home services during that same calendar month.
Both services must be related to one of the six core service areas of Maryland’s Health Home Program. Additional codes—such as W1762—have been created for this purpose. These codes further define the core service area to which the service provided belongs.
Therefore, using W1761 is not as simple as simply submitting a claim for a fixed amount each month, whether or not the individual is actively involved in the program. You must have written documentation showing the member was contacted or received services in at least two different ways as part of the core services.
And don’t forget the claim submission deadline. The claim must be submitted to the MCO or MDH within a maximum of thirty days after the end of the month in which the service was provided.
For example, if services were provided in July, the claim must be filed by August 31. If the August 31 deadline passes, the claim may be rejected for not being submitted within the required period, even if the services were actually provided.
As noted above, the same Point-of-Service (POS) rules apply equally to W1761.
| W1761 Billing Element | FY2026 Requirement |
| Procedure code | W1761 |
| Service | Monthly Health Home services |
| Reimbursement | $145.76 per month |
| Required services | Two services per month |
| Service source | Six core Health Home service areas |
| Submission deadline | Within 30 days after the end of the service month |
| OTP POS | 58, 11, 15, 49 |
| PRP POS | 11, 49, 52, 15 |
| MT POS | 11, 15, 49 |
W1762: How Health Home Services Provided in Maryland Are Identified
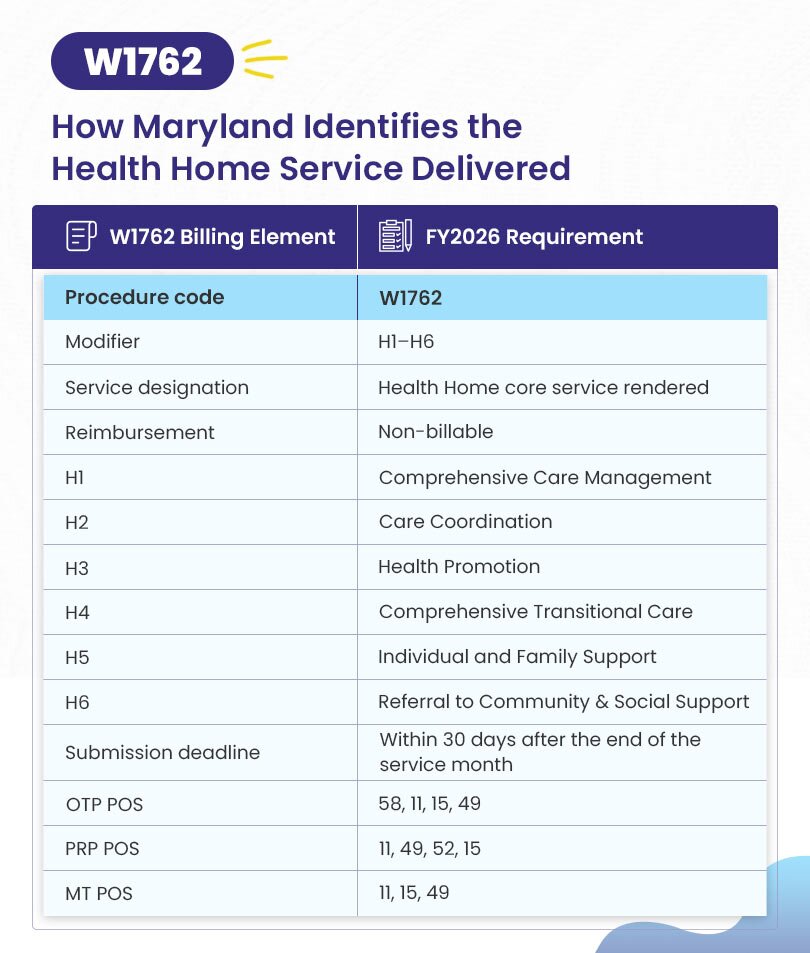
This can be confusing for some, as separate payment amounts are not offered under W1762. Instead, it serves as an identifier indicating which of the six core Health Home services was provided. On the same basis, the corresponding additional identifier codes from H1 through H6 are attached to the service entry.
See, the point here is that W1762 provides the documentation needed to satisfy the “two services” requirement under W1761.
The six core Health Home services are:
- Comprehensive care management — H1
- Care coordination — H2
- Health promotion — H3
- Comprehensive transitional care — H4
- Individual and family support — H5
- Referral to community and social support services — H6
There is a 30-day deadline for report submission. This is directly linked to your monthly W1761 payment calculation period.
So when you submit the details for your monthly payment request, you should report services that were provided during the corresponding period or services that had already been provided before the date of submission.
| W1762 Billing Element | FY2026 Requirement |
| Procedure code | W1762 |
| Modifier | H1–H6 |
| Service designation | Health Home core service performed |
| Reimbursement | Non-billable |
| H1 | Comprehensive Care Management |
| H2 | Care Coordination |
| H3 | Health Promotion |
| H4 | Comprehensive Transitional Care |
| H5 | Individual and Family Support |
| H6 | Referral to Community and Social Support |
| Submission deadline | Within 30 days after the end of the service month |
| OTP POS | 58, 11, 15, 49 |
| PRP POS | 11, 49, 52, 15 |
| MT POS | 11, 15, 49 |
W1760 vs. W1761: Same Rate, Different Payment Purpose
That’s the part where the probability of miscalculation is highest. Therefore, clearly understand the distinction: the CPT code is the same, and the Place of Service (POS) list is the same, but the rules determining payment for each are entirely different.
➜ W1760: For Member Enrollment Only
W1760 is used only once, specifically at the time of the member’s initial enrollment. Since the two-service requirement no longer applies to W1760, it does not count toward fulfilling the two-service requirement for W1761 in any given month.
Some institutions may mistakenly believe that the initial enrollment visit will count as one of the two services required by W1761. This is not the case; the two services required for W1761 must be separate from the service used to enroll the member in your program.
➜ W1761: Monthly Documentation Required
After the initial enrollment, and every month thereafter, if the member has received two qualifying core services and both are properly documented through the relevant W1762 identification codes from H1 through H6, payment under W1761 may be claimed.
Create Two Separate Triggers for Payment
There should be two distinct triggers in your billing workflow.
Trigger #1 — Initiate the Initial Payment Process
When you enroll a new member, your system should automatically generate W1760. This must be done only once for each member.
Trigger #2 — Verify Qualifying Services Monthly
Each month, it is necessary to determine how many services provided to the member meet the W1761 criteria. Based on the same assessment, decide whether or not to issue W1761.
Do Not Let Identical Rates Lead to Billing Errors
If your Electronic Health Record (EHR) or billing system treats CPT code W1761 and another code as equivalent simply because the two rates are the same and does not verify the requirement for at least two qualifying services before using W1761, this creates a significant risk.
In such a case, you may later be required to return money that has already been paid during a subsequent audit.
Pay Close Attention to Mid-Month Enrollments
Another important situation arises when a member joins your program in the middle of the month and only one qualifying service is provided before the month ends.
Based on the available information, it is not clear whether W1761 can be used in such a case.
Be Sure to Understand the Partial-Month Rule
Verify with Maryland Medicaid or MDH to determine the exact requirements for submitting a claim under W1761.
Specifically, find out whether W1761 can be billed for the first partial month and what conditions apply in that case. Also clarify whether W1761 is paid in proportion to the portion of the month used, or whether W1761 requires the full month’s service requirements to be completed.
Final confirmation of these points must come directly from Maryland Medicaid or MDH.
| Billing Factor | W1760 | W1761 |
| Service | Intake assessment or enrollment | Monthly Health Home services |
| Rate | $145.76 | $145.76 |
| Billing period | Enrollment | Monthly |
| Two-service requirement | No | Yes |
| Can intake count toward monthly requirements? | No | – |
| Function | Establishes Health Home enrollment | Reimburses ongoing monthly services |
Initial Steps for a Reimbursable Health Home Provider Agency
Your organization must complete several mandatory steps before submitting a payment request under the codes described above. All of these mandatory steps must be completed before enrolling members and submitting the first reimbursement claim.
MDH requires provider agencies to meet all of the following requirements before submitting an initial payment request.
1). Obtaining OHCQ Certification or BHA-Recognized Status for PRP, MT, or OTP Providers
Separate Maryland regulations apply to all three types of service providers: PRP, MT, and OTP.
For further details, see the relevant COMAR provisions:
Adult PRP: COMAR 10.21.21
This regulation outlines the minimum requirements for the adult psychiatric rehabilitation system. It specifies eligible individuals, the rehabilitation and support services that must be provided, and the qualifications required for staff working on those services.
Adult PRP: COMAR 10.63.03.09
This regulation establishes licensing and operational standards for the adult psychiatric rehabilitation system. It also includes required services and staff qualifications.
PRP for Minors: COMAR 10.21.29
This regulation outlines the requirements for the psychiatric rehabilitation system for minors, including mandatory services and the qualifications of staff delivering those services. It sets out the conditions under which qualified personnel provide the required rehabilitation support.
PRP for Minors: COMAR 10.63.03.10
This regulation establishes licensing and operational standards for the Psychiatric Rehabilitation Program for minors. It includes requirements for necessary staff and mandatory services.
Mobile Treatment (MT): COMAR 10.21.19
This regulation explains how the Mobile Treatment program should be operated. It covers who is eligible for these services, what services must be provided, and the qualified staff required for the program.
Mobile Treatment (MT): COMAR 10.63.03.04
This regulation details the operational and licensing standards for Mobile Treatment and Assertive Community Treatment. It addresses eligibility to participate, the services to be provided and the staffing requirements.
Opioid Treatment Program (OTP) COMAR 10.09.80
This regulation lays out Maryland Medicaid requirements for community-based substance use treatment services. It also specifies which OTP services are eligible for Medicaid reimbursement.
Opioid Treatment Program (OTP): COMAR 10.63.03.19
This rule establishes minimum operational standards for OTPs . It includes guidelines for medical supervision and the appropriate use of medication-assisted treatment, such as methadone or other approved medications, for opioid use disorder.
2). A separate National Provider Identifier (NPI) is required for each type of service-providing entity.
For example, if a PRP agency also provides MT services, it would require two separate NPIs.
To obtain a Medical Assistance (MA) Provider Enrollment Number, the applicant must submit an MA provider enrollment application and sign a provider agreement to receive a Medicaid provider identification number.
3). Submit Your Health Home Provider Application
The Health Home Provider Application must be submitted for review by email to:
4). Enrollment in eMedicaid
After enrolling in eMedicaid, your organization gets access to the Eligibility Verification System, the ability to submit payment claims electronically, and the electronic portal for Health Home documentation.
Verify the Participant’s Eligibility Before Providing Any Service
Before providing any service, the reimbursable Health Home provider organization must verify the participant’s eligibility through the Eligibility Verification System (EVS). You can log in to eMedicaid to view the participant’s eligibility information in EVS, or call 1-866-710-1447 to contact EVS directly by telephone.
Avoid This Common Error
An individual may appear as “Eligible for date of service” in EVS, leading the provider to assume that the person is also eligible for Health Home services. But that does not necessarily mean the individual qualifies.
Only individuals with full Medicaid coverage are considered eligible for Health Home services.
If the participant’s coverage description indicates any of the following, the person is not eligible for Health Home services, even though they may still appear as “Eligible” in EVS:
- The participant is an SLMB recipient.
- The participant is a QMB recipient.
- The participant’s financial benefit is limited solely to family planning services.
Who Qualifies for Maryland Health Home Services and Who Doesn’t?
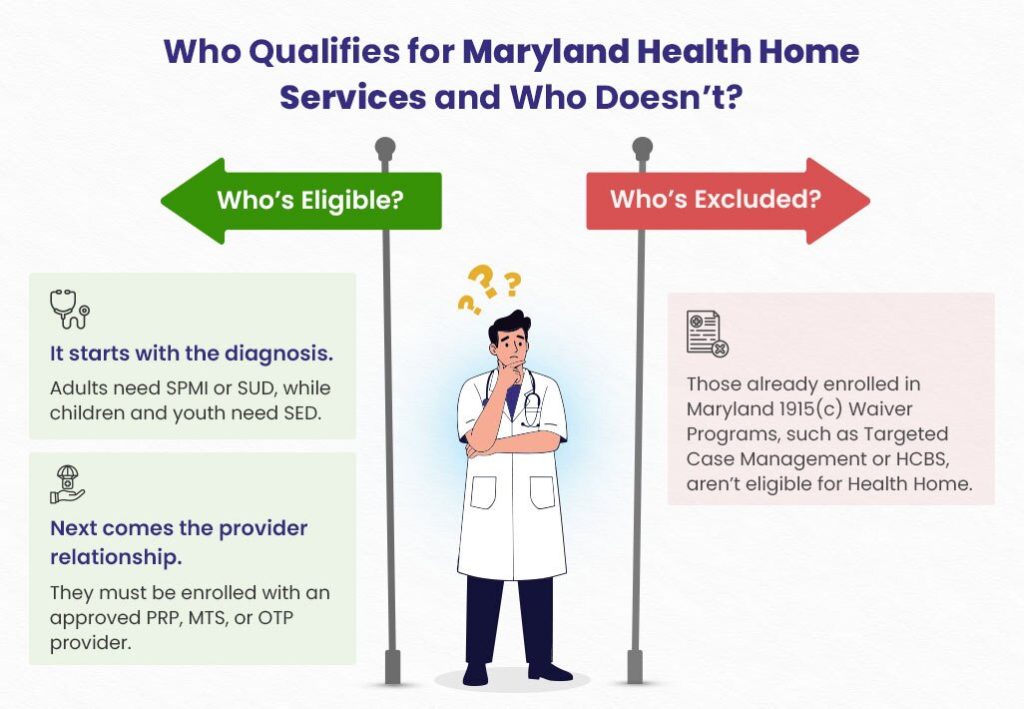
Who’s Actually Eligible?
Eligibility has basically two parts:
- the diagnosis
- the provider relationship.
For Diagnosis:
- Adults must have serious and persistent mental illness (SPMI) or a substance use disorder (SUD).
- Children and youth must have serious emotional disturbance (SED).
The person must also be enrolled with one of Maryland’s three approved Health Home provider types:
| Provider Type | Who They Serve |
| PRP (Psychiatric Rehabilitation Program) | Adults and youth with SPMI or SED |
| MTS (Mobile Treatment Services) | Individuals with serious mental illness who need intensive, community-based psychiatric care |
| OTP (Opioid Treatment Program) | Individuals with qualifying substance dependence who are enrolled in opioid treatment |
Who’s excluded?
Applicants who are currently enrolled in either of Maryland’s 1915(c) Waiver Programs, which include:
- Targeted Case Management
- Home and Community Based Services (HCBS)
These are excluded from being considered for the Health Home Program.
Maryland Health Homes: Payment Rates Apply Only When Providers Follow the Rules
It is highly likely that you will never feel the need to open and review the entire payment rate schedule from top to bottom. This is usually the need when the first payment request is rejected or the first audit letter is received. Suddenly, understanding the payment rate schedule becomes crucial.
As previously mentioned, the Maryland Health Home Program has been in operation for more than ten years. Over time, the State of Maryland has introduced various changes to clarify the conditions under which payment for accountable integrated care is considered valid. The same principles are reflected in the rules governing W1760, W1761, and W1762.
There are a few more things to keep in mind at this stage.
Using each code individually is relatively straightforward. The real complexity arises when all of them are linked together, such as member enrollment, continuous service delivery, and documented proof of those services.
Providers who treat the W1762 additional identifier codes as merely a secondary item, rather than essential evidence for a W1761 payment claim, face a higher risk of having previously paid money recouped in the future.
The rate in the payment process is only half the story. The other half consists of time-based requirements, such as the 30-day submission deadline, the 90-day waiting period before re-enrollment, the six-month restriction regarding transfers, and so on.
All of these conditions determine whether a claim that otherwise follows the rules will actually be paid.
If something in the payment rate schedule is unclear, especially when you are trying to submit a payment request for a partial month, do not rely on guesswork or assumptions. Instead, treat this as an indication that direct verification from MDH is required.
Ultimately, this entire payment rate structure is designed to ensure that the core objective of the program remains intact. Individuals facing complex mental and behavioral health problems should receive care delivered through regular coordination among different providers, rather than fragmented and disconnected care from multiple sources.



